

Understanding Asthma Triggers: A Practical Guide for Kerala Families
Dust mites, monsoon humidity, infections and exercise all provoke asthma differently — what actually triggers a flare-up, and how it is properly investigated and managed.
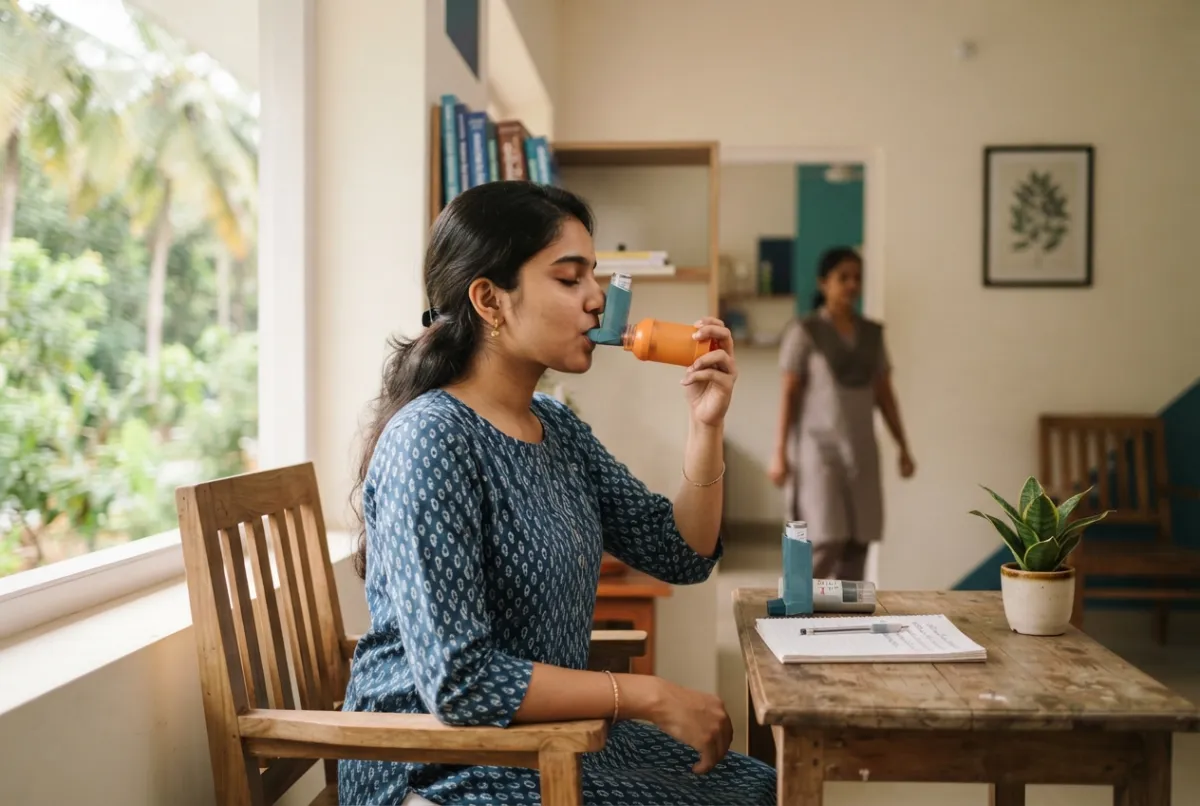
Asthma is one of the most common long-term conditions we see across our centres in Kerala, in both children and adults. It is a condition of the airways — the tubes that carry air in and out of the lungs become more sensitive than usual, and react to things that would not bother most people. When that happens, the lining of the airway swells, the muscle around it tightens, and extra mucus is produced. The result is the familiar cluster of symptoms: wheeze, breathlessness, chest tightness and cough, often worse at night or first thing in the morning.
Asthma cannot be seen on an X-ray and there is no single test that proves it on its own. A diagnosis is built from the pattern of symptoms, a physical examination, and usually a breathing test that shows how well the lungs are working and whether that improves with treatment. Getting the diagnosis right matters, because a chronic cough or breathlessness can also come from other conditions — allergic rhinitis with post-nasal drip, reflux, or a lung infection — and each of those is managed differently.
What actually triggers an asthma flare-up
No two patients have exactly the same triggers, which is part of why asthma care has to be personalised rather than generic. That said, a small number of triggers account for most of the flare-ups we see in clinic.
Indoor allergens
House dust mites are the single most common indoor trigger in our part of the world. They live in mattresses, pillows, soft furnishings and carpets, and thrive in Kerala's humidity. Pet dander, cockroach droppings and indoor mould are close behind. None of these are visible to the naked eye, which is why families are often surprised when allergy testing identifies one of them as a major driver of symptoms.
Seasonal and outdoor triggers
Pollen from grasses and weeds, sudden changes in humidity around the monsoon, and outdoor air pollution can all provoke symptoms in a sensitised airway. Some patients notice a clear seasonal pattern — worse from June to September, for instance — which is itself a useful clue when a doctor is working out what is driving the asthma.
Respiratory infections
A common cold is one of the most frequent causes of an asthma flare in both children and adults. The airway inflammation from a viral infection can persist for weeks after the cold itself has cleared, which is why a "chest infection that won't go away" is sometimes actually asthma that was never properly treated.
Exercise, weather and strong smells
Vigorous exercise, a sudden change from a warm room to cool air, smoke (including incense and mosquito coils), strong perfumes and cooking fumes are all recognised triggers. None of these need to be avoided altogether in a well-controlled patient — the goal of treatment is to reduce sensitivity to these everyday triggers, not to ask a family to avoid ordinary life.
How we investigate asthma
A first consultation usually covers a detailed history — when symptoms started, what seems to bring them on, whether there is a family history of asthma or allergy, and how symptoms affect sleep, school or work. From there, common next steps include:
- Pulmonary Function Test (PFT) — measures how much air the lungs can hold and how quickly it can be pushed out, and can show whether airflow improves after a reliever medicine is given.
- FeNO test — a simple breath test that estimates airway inflammation, useful for confirming asthma and for checking whether inhaled treatment is working.
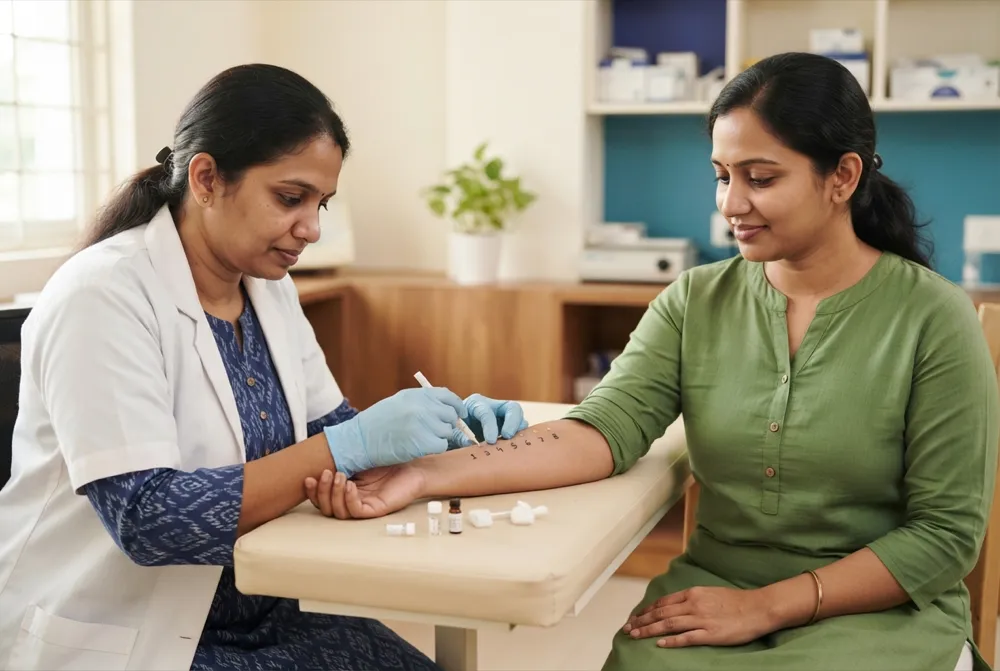
- Allergy testing — skin prick testing or a specific IgE blood test to identify which allergens, if any, are contributing.
- Forced Oscillation Technique — a breathing test that needs only quiet, normal breathing, which makes it useful for young children and older adults who cannot manage a standard spirometry manoeuvre.
Identifying a specific trigger changes the conversation from generic advice to something a family can actually act on — a particular mattress cover, a change to how a room is cleaned, or a decision to start allergen immunotherapy rather than relying on medication alone.
Living well with asthma
The aim of modern asthma care is control, not just symptom relief when things go wrong. A well-managed patient should be able to exercise, sleep through the night and go about ordinary life without frequent reliever use. A few practical habits make a real difference alongside whatever treatment a doctor prescribes:
- Wash bedding weekly in hot water and consider dust-mite-proof covers for mattresses and pillows.
- Keep humidity down where practical, and fix damp patches or mould promptly rather than just covering them over.
- Vacuum with a machine that has a good filter, and air rooms out when weather allows.
- Keep a simple diary of symptoms and possible triggers to bring to your next appointment — patterns are often easier to see on paper than to recall from memory.
- Never let a reliever inhaler be the only treatment for asthma that is happening several times a week — that is usually a sign the underlying inflammation needs to be addressed, not just the symptom.
When to seek an urgent review
Most asthma is managed calmly in an outpatient setting, but some signs mean a same-day review is needed rather than waiting for a routine appointment: breathlessness that stops someone from speaking in full sentences, blue-tinged lips or fingertips, a reliever inhaler that is not helping within the usual time, or a child who is working visibly hard to breathe. If any of these happen, do not wait — call your nearest AAF centre or go to the nearest emergency department.
Asthma is very manageable once it is properly understood. If night cough, recurrent "chest infections", or breathlessness on exertion sound familiar, it is worth having it properly assessed rather than working around it indefinitely.
This article is general patient information and does not replace a consultation. If you recognise these symptoms in yourself or your child, book an appointment so a clinician can assess your specific case.
Written by AAF Clinical Team and reviewed by the AAF clinical editorial team before publication.
Keep reading
Related health guides

Speak to a specialist, not a search bar.
Our consultants and general physicians at Perinthalmanna are available for outpatient consultations, tele-triage and personalised risk reviews.
Call Perinthalmanna: +91 88486 48396