

Living with Chronic Urticaria (Hives): Causes, Testing and Treatment
Hives that keep returning for six weeks or more need a structured work-up, not guesswork. What causes chronic urticaria, how it is tested, and how treatment is stepped up.

Chronic urticaria — hives that keep coming back, day after day, for six weeks or longer — is one of the more frustrating conditions we see, both for patients and for the clinicians treating them. The itchy, raised weals can appear anywhere on the body, often shift from one area to another within hours, and in many patients no obvious food, medicine or contact trigger can ever be found. That unpredictability is exactly why it needs a structured approach rather than trial and error at home.
What chronic urticaria actually is
Ordinary hives — the kind that appear briefly after a bee sting or an obvious food reaction — are common and usually settle on their own within hours. Chronic urticaria is different: it is defined as hives occurring on most days for six weeks or more, frequently with no identifiable external cause. When no trigger can be found, it is described as chronic spontaneous urticaria (CSU), and in a proportion of these patients the underlying process is thought to involve the immune system reacting against the body's own tissues, rather than against something from outside. This is sometimes accompanied by angioedema — deeper swelling, often around the eyes, lips or hands, which can look alarming but is usually not dangerous on its own.
What can make chronic hives worse
Even when there is no single external "cause", several everyday factors are known to worsen symptoms in patients who already have chronic urticaria:
- Heat, tight clothing or friction against the skin
- Physical or emotional stress
- Certain common painkillers, particularly some anti-inflammatory medicines
- Alcohol, and in some patients, specific foods — though true food allergy is actually an uncommon cause of chronic urticaria
- Infections, including a simple cold, which can trigger a flare in an otherwise stable patient
Because the pattern is so individual, keeping a simple diary of flares alongside daily activities, stress levels and medicines taken is one of the most useful things a patient can bring to a consultation.
How chronic urticaria is investigated
The first step is always a careful history and examination, since this is what distinguishes chronic urticaria from other skin conditions that can look similar. Depending on the pattern, a doctor may then suggest one or more of the following:
- Basic blood tests to rule out an underlying trigger such as thyroid dysfunction or an infection.
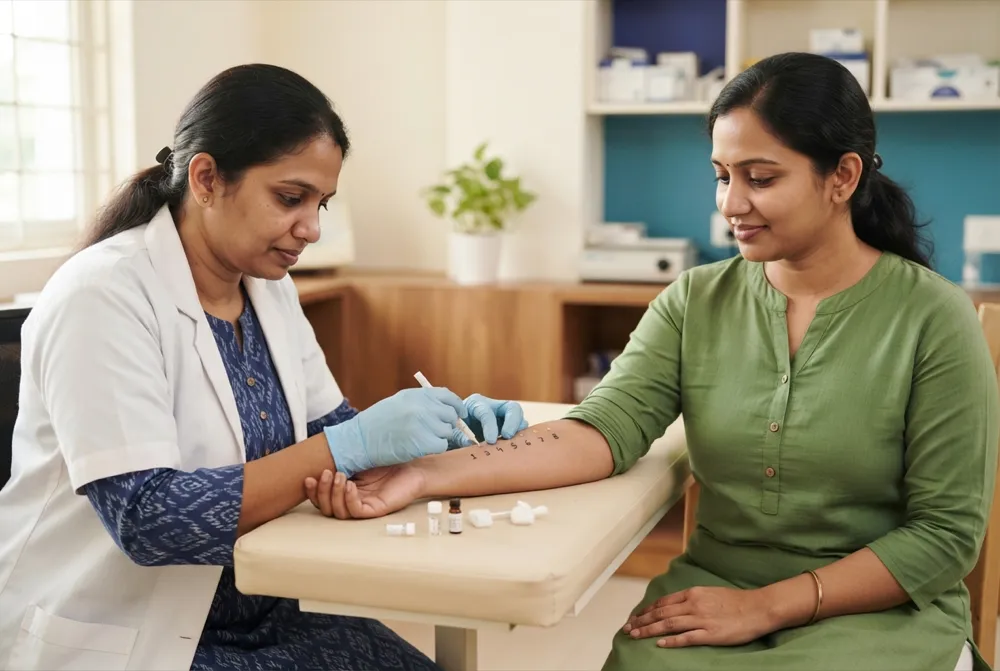
- Allergy testing — skin prick or specific IgE testing — when a genuine allergic trigger is suspected, though this is often less useful in CSU than in other allergic conditions, since most cases are not driven by a classic allergen.
- Autologous Serum Skin Test (ASST) — a test that uses a small sample of the patient's own blood serum, injected just under the skin, to look for evidence that the immune system is reacting against the body's own tissues. A positive result supports an autoimmune mechanism behind the hives and can help guide the treatment plan.
Treatment: building up in steps
Treatment for chronic urticaria is usually approached in stages, starting with the simplest effective option and stepping up only if needed:
- Non-sedating antihistamines are the first-line treatment, often at a higher dose than is used for occasional hay fever, and taken regularly rather than only when hives appear.
- Avoiding known aggravating factors such as overheating, tight clothing, or a painkiller that has been identified as a personal trigger.
- Escalating medical treatment for patients who do not settle on antihistamines alone, guided by a specialist and reviewed at regular intervals.
- Autologous Serum Therapy (AST), which uses the patient's own blood serum as an adjunctive treatment. The aim is to help desensitise the immune system over time and potentially reduce both symptoms and reliance on antihistamines. This is considered as part of an individualised plan for selected patients, alongside — not instead of — standard medical treatment.
Most patients with chronic urticaria do eventually settle, though the timeline varies considerably from one person to another, and some patients have episodes that recur months or years apart. The goal of treatment is to reduce the frequency and severity of flares and to protect quality of life in the meantime — sleep, work, and simply not having to plan around unpredictable hives.
When hives need urgent attention
Ordinary chronic urticaria is not dangerous, but certain features do need same-day medical attention: swelling of the tongue, throat tightness, difficulty breathing or swallowing, or hives appearing together with dizziness or fainting. These can be signs of a more serious, rapidly developing allergic reaction rather than ordinary chronic urticaria, and should never be managed at home.
If you have been dealing with hives that keep returning week after week, it is worth having them properly assessed. A clear diagnosis, a sensible set of tests, and a structured step-up treatment plan turn what feels like an unpredictable condition into something that can genuinely be managed.
Living with chronic urticaria day to day
Beyond medical treatment, small daily adjustments help many patients feel more in control between appointments. Loose, breathable clothing reduces friction against skin that is already irritated. Cool showers rather than hot ones, and avoiding vigorous towel-drying, can reduce the itch that often follows a flare. Keeping fingernails short limits the skin damage that comes from scratching during a bad episode, since broken skin is slower to settle and more likely to leave marks afterwards.
It also helps to have a plan agreed in advance with your clinician for what to do on a bad day — which medicine to take first, how long to wait before seeking review, and what specifically should prompt an urgent call rather than waiting it out. Patients who have this worked out in advance generally cope with flares with far less anxiety than those who are deciding what to do for the first time in the middle of an episode.
This article is general patient information and does not replace a consultation. If you recognise these symptoms in yourself or your child, book an appointment so a clinician can assess your specific case.
Written by AAF Clinical Team and reviewed by the AAF clinical editorial team before publication.
Keep reading
Related health guides
Speak to a specialist, not a search bar.
Our consultants and general physicians at Thrissur are available for outpatient consultations, tele-triage and personalised risk reviews.
Call Thrissur: +91 70125 46352